
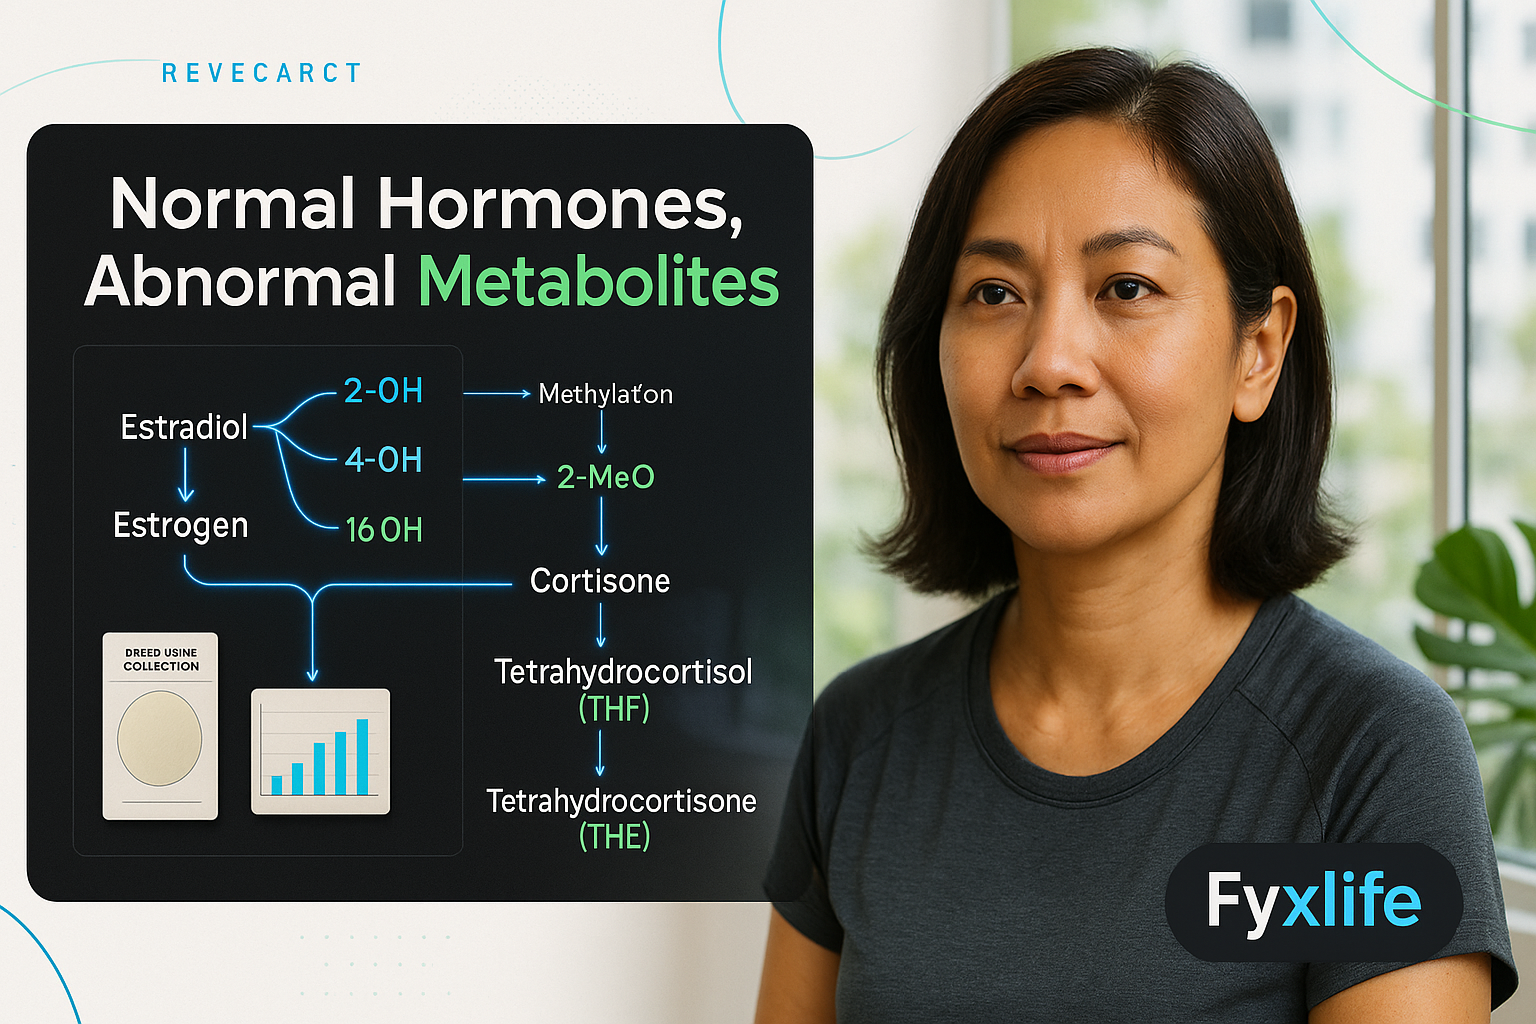
You’ve had your hormones checked. The results came back normal. And yet the fatigue, poor sleep, mood swings, and weight gain haven’t gone anywhere. The problem may not be your hormone levels — it may be what happens to those hormones after your body makes them, which standard blood tests never look at.
This is not a fringe concern or a gap only functional medicine practitioners talk about. It sits at the intersection of how hormones are produced, how they are broken down, and how the liver and gut process the resulting fragments — a picture that a single blood draw, taken at a single moment, was never designed to capture. If you have spent time chasing symptoms that your panels cannot explain, this distinction is worth understanding properly.
The Gap Between ‘Your Levels Are Normal’ and How You Actually Feel
What standard hormone blood tests measure — and what they deliberately ignore
A standard serum hormone panel measures the concentration of hormones circulating in your blood at the moment the needle goes in. Estradiol, testosterone, thyroid stimulating hormone, cortisol — these are snapshots. Useful snapshots, but snapshots nonetheless. They answer one question: how much of this hormone is in circulation right now?
What they do not answer is whether that hormone is doing what it should be doing, whether it is being processed into safe or harmful byproducts, or whether your liver and gut are handling the downstream chemistry efficiently. A clinician reviewing a standard panel can confirm that your estradiol sits within a reference range built from population averages. What they cannot tell you from that number alone is where that estradiol goes next — and that is precisely where the clinical story often becomes complicated.
The metabolite question: it’s not just how much hormone you make, it’s where it goes
Think of your hormones like a river flowing through your body. Standard blood tests measure the water level at one point in the river. The DUTCH test maps what happens downstream — whether the river flows cleanly into the sea, or backs up and floods the surrounding land. The same water level can produce very different outcomes depending on where it goes next.
Hormones do not simply disappear once they have done their job. They are broken down, or metabolised, into smaller chemical fragments — the technical term for these fragments is hormone metabolites. Some metabolites are inert. Some are mildly protective. And some, particularly certain breakdown products of estrogen, are associated with DNA damage and elevated cancer risk. Whether your body favours one pathway over another is not something a standard blood test can reveal. It requires a different method of measurement entirely.
What the DUTCH Test Actually Does
Dried urine collection — why the method matters for accuracy across a full day
The DUTCH test (Dried Urine Test for Comprehensive Hormones) works by collecting urine on filter paper at multiple points across a 24-hour period — typically four to five collections from waking through to bedtime. The samples are dried and sent to a laboratory for analysis. This method captures something a morning blood draw fundamentally cannot: hormone output and metabolite patterns across an entire day, not a single frozen moment.
Cortisol, in particular, follows a steep daily curve — high in the morning, declining through the afternoon, low at night. A single blood draw catches one point on that curve. Clinical biochemistry research documents that hormone metabolites represent a distinct and informative category from circulating hormone levels, and dried urine collection is one of the validated methods for capturing this broader picture over time.
The four hormone systems the DUTCH test maps: estrogen, progesterone, androgens, and cortisol
The DUTCH test maps four interconnected hormone systems. Estrogen is measured not just as a circulating level but through its primary breakdown pathways — revealing which metabolites your body is producing in higher quantities. Progesterone metabolites offer insight into whether progesterone production is converting appropriately. Androgens, including testosterone and its precursors, are measured alongside their metabolites to assess how active androgen signalling actually is at a tissue level, independent of what the blood shows. And cortisol is assessed both as a free circulating hormone and as its metabolised forms — a distinction that matters significantly for understanding adrenal function and fatigue.
That last point deserves emphasis. The difference between free cortisol and total cortisol metabolites is the difference between knowing how much cortisol is circulating at a moment versus understanding how much your adrenal glands are producing across the whole day. For someone presenting with persistent fatigue and a ‘normal’ cortisol blood test, this distinction can be the entire explanation.
Reading the ‘downstream’ picture — metabolites as a window into liver and gut processing
Estrogen metabolism is where the DUTCH test arguably offers its most clinically significant information. Once estrogen has circulated and done its work, the liver processes it through a series of enzymatic steps into one of several possible metabolites. The ratio between these metabolites — particularly whether estrogen is routed toward a protective form or toward a more reactive, potentially DNA-damaging form — is something peer-reviewed research on hormone metabolite testing methodologies indexes as an active area of clinical study. The same estrogen level can produce a protective or a harmful metabolic picture depending on how your liver and gut microbiome are functioning. The DUTCH test shows which route your body is taking.
Clinical nutrition research documents the relationship between metabolic status, liver processing capacity, and hormone metabolism, which helps explain why two people with identical serum estradiol readings can have meaningfully different health trajectories. One is metabolising cleanly. The other is accumulating metabolites that create ongoing biological disruption. Without looking downstream, you cannot tell which is which.
What the Research Shows — and What It Doesn’t
The clinical evidence supporting DUTCH in specific populations: PCOS, perimenopause, HRT monitoring, and metabolic dysfunction
The DUTCH test is documented in clinical practice for the assessment of menopause, polycystic ovary syndrome (PCOS), metabolic dysfunction, and hormone replacement therapy monitoring at functional medicine clinics internationally. In the context of PCOS — a condition where androgen excess, insulin resistance, and disrupted ovulation interact — the metabolite picture can clarify whether androgen levels are being amplified by poor metabolism even when serum testosterone appears borderline. In perimenopause, when hormone levels are fluctuating unpredictably rather than simply declining, the metabolite pattern often tells a more coherent story than a blood draw taken on an arbitrary day.
For those already on hormone replacement therapy, the DUTCH test’s documented use in HRT monitoring reflects its ability to track how exogenous hormones are processed — not just their circulating levels. This is a meaningful clinical distinction. Adding hormones from outside the body changes the downstream metabolite picture in ways that blood levels alone cannot predict. Ongoing and completed clinical research studies on hormone metabolite testing are searchable through ClinicalTrials.gov, indicating this is not a settled science but an actively developing one.
The honest limitations: where serum testing still outperforms, and what DUTCH cannot diagnose
Intellectual honesty requires saying this clearly: the DUTCH test is not a replacement for serum testing, and it does not diagnose anything on its own. For measuring thyroid function, for diagnosing primary endocrine disorders, for acute hormonal emergencies, and for conditions where precise real-time circulating levels matter, blood testing remains the gold standard. The clinical validation of hormone metabolite testing relative to serum testing is an area of ongoing research, and anyone who presents DUTCH results as definitive diagnostics is overstating what the evidence supports.
What the DUTCH test does well is pattern recognition — identifying tendencies in how your body processes hormones that may explain symptoms sitting outside what blood tests can account for. It generates hypotheses worth investigating. It does not close cases.
Why This Matters More If You Are in Southeast Asia
Asian metabolic risk profiles at lower BMI and earlier hormone disruption patterns
There is a broader context worth naming here. Research consistently shows that metabolic dysfunction — including insulin resistance, which directly affects how the liver processes hormones — occurs in Asian populations at significantly lower body weight thresholds than Western reference ranges assume. A BMI of 23 in a Southeast Asian adult carries metabolic risk that Western guidelines would only flag at 25 or above. Since liver function and metabolic status directly influence hormone metabolism, this matters for how you interpret your hormone picture. If your metabolic health is impaired at a weight that standard screening would consider normal, your hormone metabolite patterns may be disrupted in ways that neither your BMI nor a standard hormone panel would reveal.
Access, cost, and finding a clinician who can interpret results correctly in Singapore
In Singapore, DUTCH testing is available through a small number of functional medicine and integrative health practitioners. The test itself typically costs between SGD 500 and 900 depending on the panel, and is not covered by Medishield or most insurance schemes. The more significant cost is interpretive: the results are detailed and require a clinician who understands both the methodology and how to contextualise findings within your specific symptom picture. A DUTCH report handed to someone unfamiliar with metabolite testing will not be useful — and may generate unnecessary anxiety about numbers that represent normal variation. The challenge is that this is exactly the kind of interpretation a routine annual check-up was not designed to provide — not because doctors lack knowledge, but because a ten-minute consultation working from population-level reference ranges was never built to do this kind of personalised metabolic analysis.
What to Do With Your Results — A Plain English Translation Guide
The three numbers worth asking your doctor about first
If you do pursue DUTCH testing, three areas of the report are worth prioritising in your clinical conversation. First, the estrogen metabolite ratio — specifically the balance between the protective pathway (2-hydroxyestrone) and the more reactive pathway (16-alpha-hydroxyestrone). Second, the cortisol awakening response — the steepness of cortisol rise in the first 30 minutes after waking, which is one of the most informative single markers of how your stress response system is functioning. Third, the total cortisol metabolites versus free cortisol ratio, which distinguishes between how much cortisol your adrenals are producing and how much is actually active in circulation. These three data points, read together, will usually tell you whether metabolite testing has revealed something clinically meaningful — or confirmed that your hormone processing is functioning normally despite your symptoms pointing elsewhere.
Red flags vs. normal variation — how not to over-interpret a nuanced test
The DUTCH report is dense. It will contain numbers outside reference ranges. Some of those numbers matter. Many represent normal biological variation that requires no intervention. The critical discipline is not to treat every flagged value as a problem requiring treatment. Patterns matter more than individual data points — and patterns need to be read by someone who can also factor in your age, your symptoms, your sleep, your metabolic markers, and your life context. A single elevated metabolite ratio is not a diagnosis. It is a question worth asking. Treat the report as the beginning of a clinical conversation, not the end of one.
The One Question This Test Helps You Answer
At your next blood test review, ask your doctor for your serum estradiol and cortisol results specifically — then ask: ‘Can these results tell me how my body is processing and clearing these hormones, or only how much is circulating?’ If the answer is no, that is the precise gap the DUTCH test is designed to fill. Use that conversation to decide whether metabolite testing is worth pursuing given your specific symptoms.


